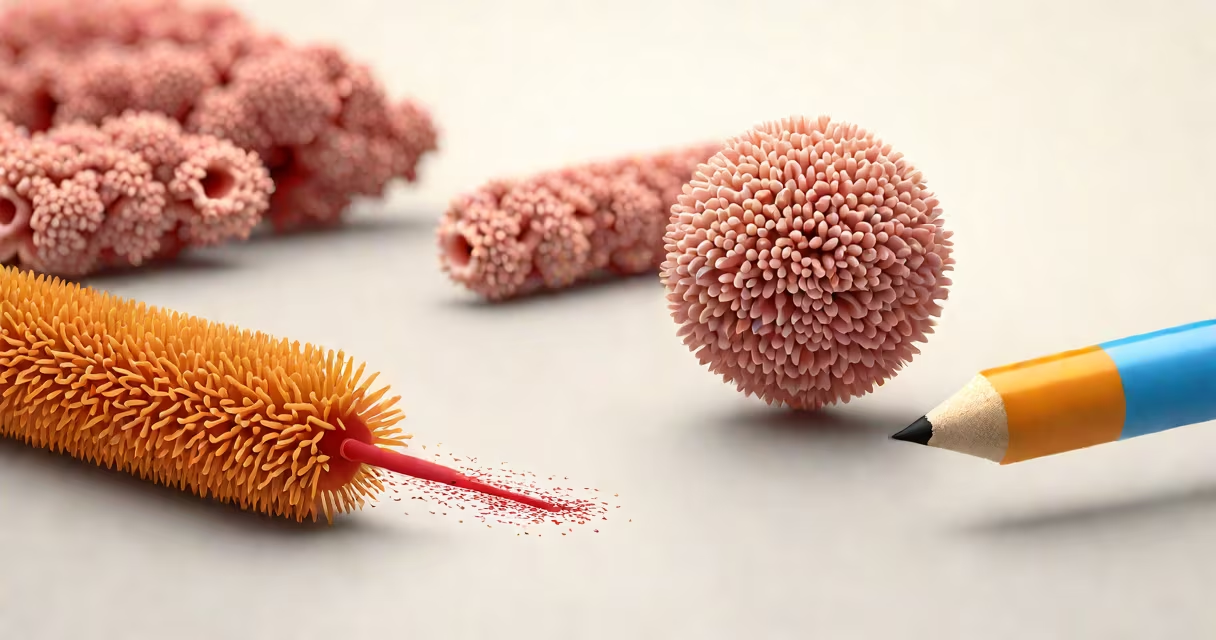
A 5 mm polyp is approximately the diameter of a standard pencil eraser-small enough to often go unnoticed during routine screening but large enough to warrant clinical attention. This size falls within the category of small adenomas detected during colonoscopy.
Polyps are abnormal growths that form on the lining of the colon or rectum. They develop from the mucosal layer and can vary widely in size, shape, and cellular makeup. A 5 mm polyp is classified as small, typically measuring between 4 and 6 millimeters in diameter. The size is measured using calibrated tools during colonoscopy or confirmed through pathology reports after removal.
According to the American Society for Gastrointestinal Endoscopy (ASGE), polyps under 6 mm have a low likelihood of harboring high-grade dysplasia or early cancer. However, even small polyps require follow-up because they can grow over time. The National Institutes of Health (NIH) notes that approximately 25% of adults aged 50 and older have at least one polyp during screening, with most being less than 10 mm.
During a colonoscopy, physicians estimate polyp size visually using reference points such as the tip of a biopsy forceps or the width of the endoscope's working channel. For accuracy, pathologists measure removed polyps under a microscope using a calibrated eyepiece. A 5 mm polyp is roughly 0.2 inches-about the thickness of a dime.
Size reporting follows standardized guidelines. The World Gastroenterology Organisation (WGO) recommends categorizing polyps as:
These categories guide surveillance intervals. A 5 mm polyp qualifies as small, which influences both treatment and follow-up decisions.
Polyp size correlates strongly with cancer risk. The risk of malignancy increases as polyps grow beyond 10 mm. A 5 mm polyp has a less than 1% chance of containing invasive cancer, according to a 2021 study published in Gastroenterology. This is based on analysis of over 10,000 polyps from national screening databases.
However, size alone doesn't determine risk. Histology-the microscopic appearance-is equally important. A 5 mm polyp may be a hyperplastic polyp (benign, no cancer risk) or a tubular adenoma (pre-cancerous, requiring removal). Only pathology examination confirms the type.
For example, in a 2020 cohort study from the Mayo Clinic, 14% of 5 mm polyps were adenomatous. These were removed and showed no evidence of dysplasia. The study concluded that while small polyps pose minimal immediate threat, their presence signals a higher lifetime risk of colorectal cancer.
Many patients assume that any polyp, regardless of size, requires urgent treatment. This is incorrect. A 5 mm polyp is often managed conservatively-removed during colonoscopy if accessible, then monitored via repeat screening in 5 to 10 years.
Another misconception is that size determines whether a polyp is "cancer." A 5 mm polyp cannot be cancer. Cancer develops from cells that grow abnormally over time. A 5 mm polyp may contain precancerous changes, but it is not cancer itself. The term "precancerous" applies to adenomas, not to all polyps.
One non-obvious fact: size is not always proportional to risk. A 5 mm flat polyp has a higher chance of containing dysplasia than a 5 mm pedunculated (stalked) polyp. Flat lesions are harder to detect and more likely to progress silently. The ASGE warns that flat morphology increases risk independent of size.
Consider a 58-year-old patient undergoing routine colonoscopy. The gastroenterologist identifies a 5 mm polyp in the sigmoid colon. It appears slightly raised and has a smooth surface. The physician removes it using a snare and sends it to pathology.
Pathology results confirm it is a tubular adenoma with low-grade dysplasia. The patient is advised to return for a follow-up colonoscopy in 10 years. No further treatment is needed. This outcome reflects standard care for small polyps with low-risk features.
If the same polyp had been 12 mm, the recommendation would have changed. Surveillance would occur in 3 years due to increased risk of recurrence and progression. Size matters-but so do location, shape, and histology.
After polyp removal, the timing of the next colonoscopy depends on multiple factors. For a single 5 mm adenoma with no dysplasia, the American Cancer Society recommends a repeat exam in 10 years. If the polyp was flat or had high-grade dysplasia, the interval shortens to 3 years.
Patients should not assume that a small polyp means no future risk. The presence of any polyp increases the likelihood of developing new ones. Long-term surveillance is essential. The NIH reports that individuals with one adenoma have a 30% chance of developing another within five years.
I've seen this pattern firsthand during my time assisting in outpatient GI clinics. A patient returned six years after a 5 mm polyp removal, only to find a 10 mm polyp in the same area. Early detection and consistent follow-up prevented progression to cancer.
To visualize 5 mm, compare it to everyday objects:
| Object | Size in mm | Visual Reference |
|---|---|---|
| Pencil eraser | 5 mm | Standard size |
| Dime (U.S.) | 17.9 mm | More than triple the size |
| Grain of rice | 3-5 mm | Similar range |
| Pinhead | 1-2 mm | Smaller than 5 mm |
These comparisons help patients understand that a 5 mm polyp is not large by medical standards-but it is significant enough to monitor.